

DOSING OPTIONS BUILT FOR PATIENT FLEXIBILITY
Infusion flexibility
Optimize patient experience with flexible dosing options
With Hizentra, there are multiple parameters that can be tailored to your individual patients’ needs.
Infusion volume
Patients infuse less volume per infusion with Hizentra than with 10% Ig products
Infusion frequency
Biweekly, weekly, or frequent dosing (2-7 times/week) options are available
Infusion duration
Total infusion time may vary based on the infusion parameters selected and patient tolerability
Number of infusion sites
In the US study, most infusions required 4 or fewer sites
DOSING CALCULATOR
PI patient dosing calculator
Calculate Weekly Dose
*To convert the patient's current IVIg 10% dose from milliliters to grams, divide the milliliters by 10.
Dosing Results
Based on an IVIg dose of 0.00 g every 0 week(s), your Hizentra dose every 0 day(s) will be:
To determine a weekly dose when switching from IVIg, the calculator uses the following formula:
Initial weekly recommended dose of Hizentra =
Previous IVIg dose (g)
Number of weeks between scheduled IVIg doses
When switching from a different SCIg product to Hizentra, the previous weekly SCIg dose (g) should be maintained.
Formulas for dosing adjustments
| Dosing Schedule | Start Hizentra | Dosing |
| Biweekly | 1 or 2 weeks after last IVIg infusion or 1 week after the last weekly SCIg infusion | Administer twice the calculated weekly dose from above |
| Weekly | 1 week after last IVIg or SCIg infusion | Administer the calculated weekly dose |
| Frequent (2x-7x/week) | 1 week after last IVIg or SCIg infusion | Divide the calculated weekly dose by the desired number of infusions per week |
Dosing Schedule
Start Hizentra
1 or 2 weeks after last IVIg infusion or 1 week after the last weekly SCIg infusion
Dosing
Administer twice the calculated weekly dose from above
Start Hizentra
1 week after last IVIg or SCIg infusion
Dosing
Administer the calculated weekly dose
Start Hizentra
1 week after last IVIg or SCIg infusion
Dosing
Divide the calculated weekly dose by the desired number of infusions per week
Formulas for dosing adjustments
every-2-weeks dose =
FREQUENT DOSE =
Weekly dose
Number of doses/week
| Infusion parameters† | 1st infusion | Subsequent infusions |
| Volume g/site (mL/site) | ≤3 (≤15) | ≤5 (≤25) |
| Rate g/hr/site (mL/hr/site) | ≤3 (≤15) | ≤5 (≤25) |
†As tolerated. Volumes and flow rates suggested are per each infusion site chosen.
Personalization Examples
Examples of treatment personalization
See sample dosing schedules that accommodate clinical needs and patient preference and tolerability

WHY HIZENTRA?
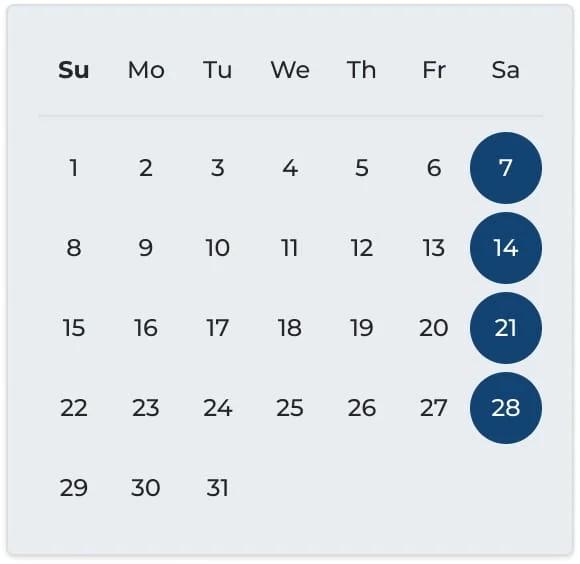
SCIg offers more frequent, lower volume infusions and more consistent steady-state Ig levels compared to IVIg. This may help reduce the occurrence of systemic AEs.
Dose: 14 g/70 mL, once a week
Infusion sites: 3‡
Time per infusion§: ~1 hour

WHY HIZENTRA?
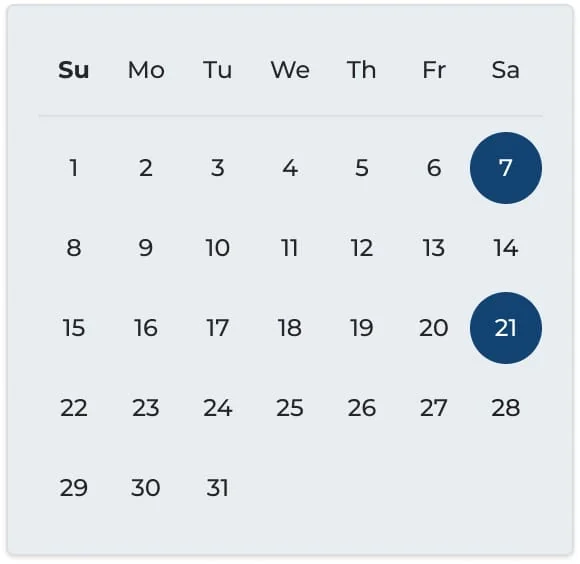
Subcutaneous self-administration means no more difficulties finding a vein or needing a port.
Dose: 16 g/80 mL, once every 2 weeks
Infusion sites: 4‡
Time per infusion§: ~48 minutes

WHY HIZENTRA?
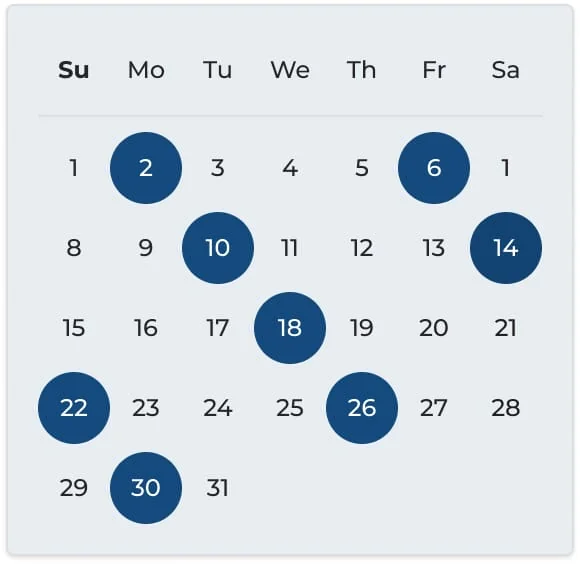
Infusing at home means no more trips to the infusion clinic and not missing school or activities each month.
Dose: 6 g/30 mL, twice a week
Infusion sites: 2‡
Time per infusion§: ~36 minutes

WHY HIZENTRA?
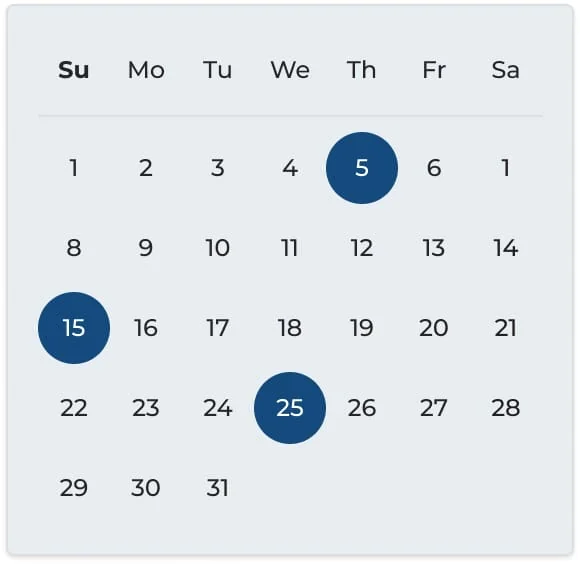
Flexible dosing with a personalized self-infusion schedule means no more working around infusion nurse visits, accommodating the needs of a busy life.
Dose: 10 g/50 mL, every 10 days
Infusion sites: 2‡
Time per infusion§: ~1 hour
Case studies do not depict actual patients.
‡Rate of infusion and number of infusion sites in these hypothetical case studies are based on recommended rate and volume per site of subsequent infusions.
§Infusion time may be shorter or longer depending on the dose, frequency, and ancillary supplies utilized.
Abbreviations: AE, adverse event; Ig, immunoglobulin; IVIg, intravenous immunoglobulin; PI, primary immunodeficiency; SCIg, subcutaneous immunoglobulin.
References: 1. Wasserman RL, Melamed I, Nelson RP Jr, et al. Clin Pharmacokinet. 2011;50(6):405-414. doi:10.2165/11587030-000000000-00000 2. Jolles S, Rojavin MA, Lawo JP, et al. J Clin Immunol. 2018;38(8):864-875. doi:10.1007/s10875-018-0560-5 3. Berger M. Curr Opin Allergy Clin Immunol. 2011;11(6):532-538. doi:10.1097/ACI.0b013e32834c22da 4. Immune Deficiency Foundation. Treatment experiences and preferences of patients with primary immune deficiency diseases: first national, survey. June 20, 2003. Accessed July 1, 2026. https://primaryimmune.org/resources/print-material/first-national-survey-2003 5. Berger M. Immunotherapy. 2014;6(1):71-83. doi:10.2217/IMT.13.146
IMPORTANT SAFETY INFORMATION
WARNING: Thrombosis may occur with immune globulin products, including Hizentra. Risk factors may include: advanced age, prolonged immobilization, hypercoagulable conditions, history of venous or arterial thrombosis, use of estrogens, indwelling vascular catheters, hyperviscosity, and cardiovascular risk factors.
For patients at risk of thrombosis, administer Hizentra at the minimum dose and infusion rate practicable. Ensure adequate hydration in patients before administration. Monitor for signs and symptoms of thrombosis and assess blood viscosity in patients at risk for hyperviscosity.
Hizentra is contraindicated in patients with a history of anaphylactic or severe systemic reaction to human immune globulin (Ig) or components of Hizentra (eg, polysorbate 80), as well as in patients with immunoglobulin A deficiency with antibodies against IgA and a history of hypersensitivity. Because Hizentra contains L-proline as stabilizer, use in patients with hyperprolinemia is contraindicated.
IgA-deficient patients with anti-IgA antibodies are at greater risk of severe hypersensitivity and anaphylactic reactions. Thrombosis may occur following treatment with Ig products, including Hizentra.
Monitor patients for aseptic meningitis syndrome (AMS), which may occur following treatment with Ig products, including Hizentra. In patients at risk of acute renal failure, monitor renal function, including blood urea nitrogen, serum creatinine and urine output. In addition, monitor patients for clinical signs of hemolysis or pulmonary adverse reactions (eg, transfusion-related acute lung injury [TRALI]).
Hizentra is derived from human blood. The risk of transmission of infectious agents, including viruses and, theoretically, the Creutzfeldt-Jakob disease (CJD) agent and its variant (vCJD), cannot be completely eliminated.
The most common adverse reactions (observed in ≥5% of study subjects) were local infusion-site reactions, as well as headache, diarrhea, fatigue, back pain, nausea, extremity pain, cough, upper respiratory tract infection, rash, pruritus, vomiting, upper abdominal pain, migraine, arthralgia, pain, fall, and nasopharyngitis.
The passive transfer of antibodies can interfere with response to live virus vaccines and lead to misinterpretation of serologic test results.
Indications
Hizentra®, Immune Globulin Subcutaneous (Human), 20% Liquid, is indicated for:
- Treatment of primary immunodeficiency (PI) in adults and pediatric patients 2 years and older.
- Maintenance therapy in adults with chronic inflammatory demyelinating polyneuropathy (CIDP) to prevent relapse of neuromuscular disability and impairment.
- Limitation of Use: Maintenance therapy in CIDP has been systematically studied for 6 months and for a further 12 months in a follow-up study. Continued maintenance beyond these periods should be individualized based on patient response and need for continued therapy.
For subcutaneous infusion only.
Please see full Prescribing Information for Hizentra including boxed warning.
To report SUSPECTED ADVERSE REACTIONS, contact the CSL Behring Pharmacovigilance Department at 1-866-915-6958 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.

Hizentra is manufactured by CSL Behring AG and distributed by CSL Behring LLC.
Hizentra® is a registered trademark of CSL Behring AG.
Hizentra Connect℠ is a service mark of CSL Behring LLC.